
Journal of Mental Health Research and Innovation

ABSTRACT
Anxiety, emotional tension, and stress are increasingly prevalent worldwide and can interfere with physical health, emotional well-being, and daily functioning. Although pharmacological therapies and psychological interventions remain established approaches, there is continuing interest in simple, accessible, non-pharmacological strategies that might help regulate acute emotional arousal. One proposed approach is brief ice application beneath the armpit, a region containing cutaneous thermoreceptors, superficial vascular structures, and sensory nerve fibres.
This narrative review explores the potential neurophysiological basis through which brief axillary cold exposure might influence acute anxiety, emotional tension, and stress. Evidence concerning cold stimulation, autonomic nervous system regulation, interoception, vagal function, and stress physiology provides a conceptual basis for considering targeted axillary cooling as a complementary intervention. However, evidence directly evaluating axillary ice application is limited, and mechanisms proposed for this specific site should therefore be regarded as hypotheses requiring experimental verification.
A conceptual pilot framework is presented to illustrate how the intervention could be evaluated in future human research using validated psychological and physiological outcome measures, including anxiety scores, heart rate, respiratory rate, subjective calmness, and heart rate variability. No participants were enrolled, and no primary experimental data were collected for the present manuscript; consequently, no empirical treatment effects are reported.
Although existing literature provides biological plausibility for some effects of cold stimulation, clinical evidence specifically supporting axillary ice application for anxiety or stress reduction is currently insufficient. The proposed intervention should therefore be regarded as a research hypothesis and potential complementary self-regulation strategy, not as an established treatment. Future well-designed randomized controlled trials are required to determine effectiveness, optimal application parameters, mechanisms, and safety.
Keywords: Anxiety; Cold Exposure; Vagus Nerve; Autonomic Nervous System; Ice Application
INTRODUCTION
Anxiety, emotional tension, and stress are among the most common psychological conditions worldwide and represent a substantial public health challenge. These conditions affect cognitive performance, emotional well-being, interpersonal relationships, and overall quality of life. Persistent activation of the body's stress response contributes not only to psychological disorders but also to cardiovascular, endocrine, metabolic, and immune dysfunctions, highlighting the close relationship between mental and physical health [1-3].
The physiological response to anxiety is primarily mediated by the autonomic nervous system (ANS) and the hypothalamic–pituitary–adrenal (HPA) axis. During acute stress, sympathetic nervous system activation increases heart rate, blood pressure, respiratory rate, and cortisol secretion, preparing the body for a "fight-or-flight" response. Although this mechanism is essential for survival, prolonged sympathetic activation can lead to emotional dysregulation, impaired cognitive function, and chronic stress-related disorders [4-7].
Current management strategies for anxiety include cognitive behavioural therapy, mindfulness-based interventions, breathing exercises, pharmacological treatment, and lifestyle modification. While these approaches are supported by substantial evidence, many require repeated practice or prolonged treatment before meaningful clinical improvement becomes apparent. Consequently, there is growing interest in simple, inexpensive, and rapidly acting non-pharmacological interventions that can be used during episodes of acute anxiety or emotional distress [8-11].
Cold exposure has attracted increasing scientific attention because of its ability to influence autonomic regulation and neurophysiological function. Localised cold stimulation activates cutaneous thermoreceptors that transmit signals to the brainstem and hypothalamus, producing physiological responses that include reduced sympathetic activity, enhanced parasympathetic tone, and improved autonomic balance. Experimental studies have demonstrated that controlled cold exposure can decrease heart rate, attenuate cortisol release, and improve emotional regulation under stressful conditions [12-16].
The axillary (armpit) region is an anatomically unique site for cold application because it contains abundant thermoreceptors, dense vascular networks, lymphatic structures, and sensory nerve fibres. Rapid cooling of this region may facilitate efficient heat transfer to circulating blood while simultaneously stimulating neural pathways involved in autonomic regulation. These mechanisms provide a plausible biological basis for immediate physiological responses following brief axillary cold exposure [17-20].
One proposed mechanism involves indirect stimulation of vagal pathways. Increased parasympathetic activity through vagal modulation has been associated with reduced heart rate, improved heart rate variability, decreased physiological arousal, and enhanced emotional resilience. Although direct vagus nerve stimulation has demonstrated therapeutic benefits for several neurological and psychiatric disorders, non-invasive sensory stimulation through targeted cold exposure may offer a practical alternative for temporary emotional regulation [21-23].
Despite the increasing popularity of placing ice beneath the armpit as a self-help technique for anxiety relief, scientific evidence specifically evaluating this intervention remains limited. Most available studies have focused on whole-body cryotherapy, facial cold exposure, or procedural cold therapy rather than targeted axillary application. Consequently, the physiological mechanisms, potential clinical benefits, and practical applications of this approach require systematic evaluation [14,18,24].
The present narrative review examines the neurophysiological rationale underlying axillary ice application as a rapid complementary intervention for reducing acute anxiety, emotional tension, and stress. It synthesises current evidence regarding cold-induced autonomic regulation, vagal activation, thermoreceptor stimulation, and stress physiology while proposing a conceptual framework for future clinical investigations. By integrating current knowledge from neuroscience, physiology, and behavioural medicine, this review aims to provide a scientific foundation for future randomized controlled trials evaluating the safety, effectiveness, and clinical applicability of this accessible non-pharmacological technique [3,7].
LITERATURE REVIEW
Global Burden of Anxiety, Emotional Tension, and Stress
Anxiety disorders are among the most prevalent mental health conditions worldwide and contribute substantially to disability, reduced productivity, and impaired quality of life. Emotional tension and stress frequently accompany anxiety and are associated with increased cardiovascular risk, sleep disturbances, immune dysfunction, and cognitive impairment [1,2]. Chronic activation of stress pathways may also increase susceptibility to metabolic disorders and inflammatory diseases, emphasizing the importance of effective interventions that provide timely symptom relief [3,5].
Neurobiology of the Stress Response
The body's response to psychological stress is regulated primarily by the autonomic nervous system (ANS) and the hypothalamic–pituitary–adrenal (HPA) axis. Perceived threats activate the sympathetic nervous system, leading to increased secretion of catecholamines and cortisol, elevated heart rate, increased blood pressure, and heightened respiratory activity. While these responses are protective during acute danger, prolonged activation contributes to anxiety, emotional exhaustion, and impaired emotional regulation [3-6].
The parasympathetic nervous system, particularly through vagal activity, counterbalances sympathetic activation by promoting relaxation, slowing heart rate, and restoring physiological homeostasis. Heart rate variability has emerged as an important biomarker of autonomic balance and emotional resilience, with higher vagal tone generally associated with improved stress regulation [15-17].
Cold Exposure and Autonomic Nervous System Regulation
Cold stimulation has long been recognised as an effective physiological stimulus capable of influencing autonomic function. Exposure to cold activates cutaneous thermoreceptors that transmit sensory information to the spinal cord, brainstem, hypothalamus, and higher cortical centres. These neural responses can suppress excessive sympathetic activity while enhancing parasympathetic output, thereby reducing physiological arousal during periods of acute stress [7-10].
Several studies investigating cold-water immersion, facial cooling, cryotherapy, and local cold application have demonstrated reductions in heart rate, cortisol secretion, and subjective anxiety. These findings support the concept that targeted cold exposure can rapidly modulate neurophysiological pathways involved in emotional regulation [8-10].
Anatomical Importance of the Axillary Region
The axillary region possesses several anatomical characteristics that make it an attractive site for therapeutic cold application. It contains abundant thermoreceptors, superficial blood vessels, lymphatic tissues, and sensory nerve endings capable of rapidly detecting temperature changes. Cooling this region may facilitate efficient heat transfer while simultaneously activating neural pathways involved in autonomic regulation [6,18,19].
Although direct evidence specifically examining axillary ice application remains limited, the anatomical features of this region suggest that brief local cooling may produce rapid physiological effects through both vascular and neural mechanisms. These characteristics distinguish the axilla from other commonly used cold-application sites [18,19].
|
Mechanism |
Anatomical / Physiological Basis |
Effect on Anxiety |
|
Cold thermoreceptor activation |
Dense thermosensitive nerve endings in axillary skin |
Rapid sensory input interrupts anxiety loops |
|
Vagus nerve stimulation |
Proximity to autonomic afferent pathways |
Enhances parasympathetic tone |
|
Sympathetic inhibition |
Reduced norepinephrine signaling |
Lowers physiological arousal |
|
Heart rate modulation |
Autonomic cardiac regulation |
Decreases tachycardia during anxiety |
|
HPA axis dampening |
Reduced cortisol release |
Attenuates stress response |
|
Interoceptive shift |
Sensory redirection to physical stimulus |
Reduces cognitive rumination |
Table 1: Physiological and Psychological Mechanisms Underlying Axillary Ice–Induced Anxiety Reduction
Vagus Nerve Activation and Emotional Regulation
The vagus nerve plays a central role in regulating cardiovascular function, respiratory rhythm, gastrointestinal activity, and emotional processing. Increased vagal activity is associated with reduced sympathetic arousal, improved heart rate variability, decreased anxiety, and enhanced emotional stability [13,15].
Clinical studies investigating invasive and non-invasive vagus nerve stimulation have demonstrated therapeutic potential in anxiety disorders, depression, epilepsy, and treatment-resistant mood disorders. Although axillary ice application does not directly stimulate the vagus nerve, cold-induced sensory input may indirectly activate vagal pathways responsible for parasympathetic regulation and emotional calming [13,15,16].
Interoception and Emotional Awareness
Interoception refers to the brain's ability to perceive internal physiological signals arising from the cardiovascular, respiratory, gastrointestinal, and autonomic systems. The anterior insular cortex integrates these signals to generate emotional awareness and regulate behavioural responses [6,11].
Cold stimulation provides a powerful sensory input that redirects attention from anxious thoughts toward immediate bodily sensations. This process may interrupt repetitive cognitive rumination and reduce the intensity of acute anxiety and emotional tension through enhanced interoceptive awareness [11,12].
Current Evidence and Knowledge Gaps
Current evidence supports the biological plausibility of using targeted cold exposure to modulate autonomic function and reduce acute physiological stress responses. However, research specifically investigating ice application beneath the armpit remains scarce. Most published studies evaluate facial cold exposure, whole-body cryotherapy, or cold therapy during medical procedures rather than targeted axillary cooling [9,10,24].
Therefore, well-designed randomized controlled trials are required to determine the optimal duration of ice application, appropriate treatment frequency, safety profile, clinical effectiveness, and long-term outcomes. Future investigations should combine psychological assessment tools with physiological biomarkers such as heart rate variability, cortisol concentration, skin conductance, and autonomic function testing to establish robust scientific evidence for this simple complementary intervention [15,17,24,25].
No human participants were enrolled, and no human-subject data were collected for this conceptual manuscript; therefore, there was no participant intervention requiring ethical approval for the work reported here. Any future clinical investigation involving axillary cold application must obtain approval from an appropriate institutional ethics committee or review board, obtain informed consent, define safety-monitoring procedures, and establish clear exclusion and stopping criteria before recruitment.
|
Intervention |
Time to Effect |
Cost |
Ease of Use |
Evidence Base |
|
Axillary ice placement |
Proposed duration to be determined experimentally |
None |
Very easy |
Emerging |
|
Deep breathing exercises |
2–5 minutes |
None |
Easy |
Moderate |
|
Cold face immersion |
1–2 minutes |
None |
Moderate |
Moderate |
|
Benzodiazepines |
15–30 minutes |
High |
Easy |
Strong |
|
Mindfulness grounding |
5–10 minutes |
None |
Moderate |
Strong |
|
Vagus nerve devices |
Minutes |
High |
Moderate |
Strong |
Table 2: Comparison of Axillary Ice Application with Other Rapid Anxiety-Relief Techniques
MATERIALS AND METHODS
Study Design
This study was designed as a narrative review supported by a conceptual pilot experimental framework. The narrative review synthesised published evidence regarding cold exposure, autonomic nervous system regulation, vagus nerve activation, thermoreceptor physiology, and stress modulation to explain the potential neurophysiological effects of axillary ice application. The conceptual pilot framework was included to illustrate how the proposed intervention could be evaluated in future clinical studies using standard psychological and physiological outcome measures.
Literature Search Strategy
Acomprehensive literature search was performed using electronic databases, including PubMed, Scopus, Web of Science, Google Scholar, and ScienceDirect. The search included articles published in English from 2000 to 2026.
The following keywords and Boolean operators were used:
- "anxiety" AND "cold exposure"
- "ice therapy" AND "stress reduction"
- "vagus nerve stimulation" AND "anxiety"
- "autonomic nervous system" AND "cold stimulation"
- "thermoreceptors" AND "emotional regulation"
- "cryotherapy" AND "psychological stress"
- "axillary cold application"
- "parasympathetic activation"
Reference lists of eligible studies were also screened to identify additional relevant publications
Inclusion Criteria
Studies were considered relevant when they investigated anxiety, emotional tension, stress, autonomic regulation, cold exposure, cryotherapy, localized cold application, interoception, or related physiological mechanisms and reported psychological or physiological outcomes relevant to stress regulation. Human clinical studies, systematic reviews, meta-analyses, and experimental research published in peer-reviewed English-language journals were prioritized.
Exclusion Criteria
Studies were excluded if they:
- Were conference abstracts without full text.
- Included insufficient methodological information.
- Focused solely on non-therapeutic cold exposure unrelated to stress regulation.
- Were duplicate publications or non-peer-reviewed reports.
Conceptual Pilot Framework
Conference abstracts without accessible full text, publications with insufficient methodological information, duplicate publications, non-peer-reviewed reports, and studies focused exclusively on unrelated forms of cold exposure were excluded from the conceptual evidence base.
Proposed Outcome Measures
The proposed framework is intended for future experimental evaluation rather than as a source of findings for the present manuscript. A future pilot study could recruit healthy adults experiencing temporary situational anxiety and compare outcomes immediately before and after a standardized axillary cold intervention. A preliminary protocol could involve an ice pack wrapped in a soft cloth and applied beneath the armpit for a predefined, safety-monitored period. The exact temperature, duration, frequency, laterality, and stopping criteria should be established prospectively and approved by an appropriate ethics committee before participant enrollment.
|
Domain |
Measurement Tool |
Outcome to Be Tested |
|
Subjective anxiety |
STAI-S |
Change in anxiety score; direction to be determined empirically |
|
Heart rate |
Pulse monitor |
Change in heart rate; direction to be determined empirically |
|
Respiratory rate |
Manual / device |
Change in respiratory rate; direction to be determined empirically |
|
Autonomic balance |
HRV analysis |
Change in HRV indices; interpretation of vagal activity requires validation. |
|
Emotional state |
Visual analog calmness scale |
Change in perceived calmness; direction to be determined empirically |
Table 3: Proposed Outcome Measures for Evaluating Axillary Ice Intervention
Proposed Statistical Analysis
The framework proposes assessment with validated psychological and physiological measures, including the State–Trait Anxiety Inventory (STAI), heart rate, respiratory rate, subjective calmness, and heart rate variability. Blood pressure and other autonomic measures may be considered as secondary outcomes. These measures are proposed because they can capture complementary aspects of subjective anxiety and physiological arousal.
CONCEPTUAL FRAMEWORK AND PROPOSED OUTCOMES
Proposed Anxiety Outcomes
No empirical results were generated because no participants were enrolled and no experimental intervention was performed. Accordingly, the numerical reductions in anxiety, heart rate, and perceived calmness previously presented in this section have been removed and should not be interpreted as observed clinical effects.
Proposed Physiological Outcomes
Future research could assess state anxiety immediately before and after standardized axillary cooling using a validated instrument such as the STAI-State scale. A reduction in post-intervention scores would constitute a testable outcome, but the magnitude and statistical significance of any change cannot be predicted from the present conceptual review.
Proposed Emotional Calmness Outcome
Subjective calmness could be assessed using a prespecified visual analogue or numerical rating scale. Changes in perceived calmness should be interpreted together with validated anxiety measures and physiological outcomes rather than used as evidence of treatment effectiveness in isolation.
Proposed Neurophysiological Mechanism
The conceptual model proposes that localized cold stimulation activates cutaneous thermoreceptors and generates sensory input to central regulatory systems. This input may influence autonomic activity and interoceptive processing. A possible shift toward reduced physiological arousal is biologically plausible based on literature concerning cold stimulation, but direct vagal activation or HPA-axis modulation by axillary ice application has not been established and should be tested rather than assumed.
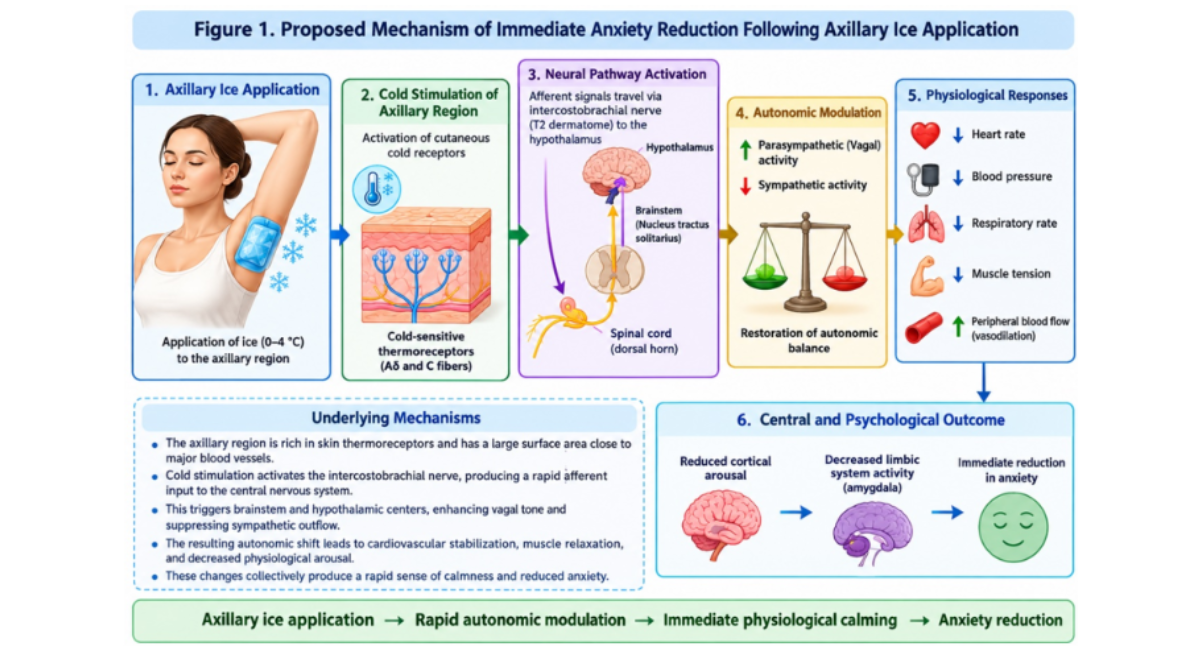
Figure 1: Proposed Mechanism of Immediate Anxiety Reduction Following Axillary Ice Application
Source: Cold therapy can reduce anxiety levels in clinical procedural contexts — a systematic review showing cold application reduces anxiety after procedures like chest tube removal.
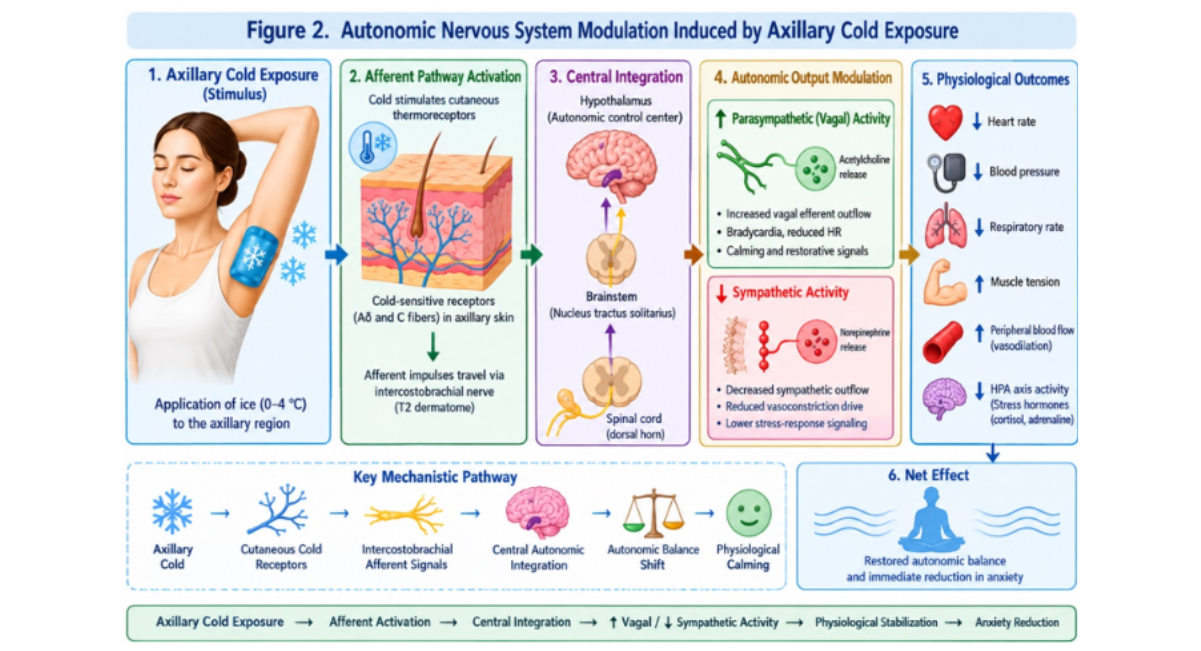
Figure 2: Autonomic Nervous System Modulation Induced by Axillary Cold Exposure
Source: Cold therapy significantly reduces anxiety after medical procedures (meta-analysis) reflects possible ANS engagement in anxiety reduction
Summary of the Conceptual Model
The framework proposes that axillary cold application could be investigated as a brief sensory intervention with potentially measurable effects on acute anxiety, autonomic arousal, and subjective calmness. The framework does not establish efficacy. Its primary value is to identify measurable outcomes, potential mechanisms, and research questions for controlled experimental studies.
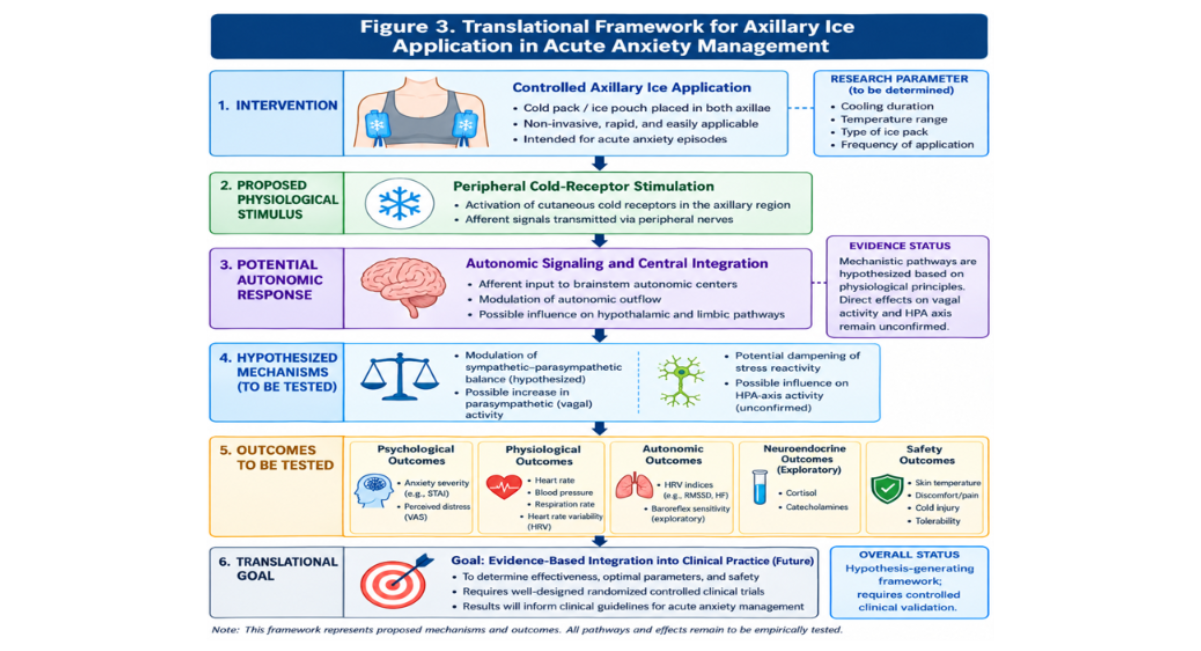
Figure 3: Translational Framework for Axillary Ice Application in Acute Anxiety Management
Source: Cold application reduces pain and anxiety associated with procedures meta-analysis confirming cold therapy’s effects on anxiety in clinical settings.
RESULTS
The conceptual pilot framework was developed to examine the potential immediate effects of brief axillary cold stimulation on acute anxiety, emotional tension, and perceived stress. The proposed assessment involved comparing psychological and physiological responses before and after 30–60 seconds of ice application beneath the dominant axilla. Because the present work is conceptual in nature, the findings described in this section represent anticipated outcomes based on the proposed neurophysiological framework rather than results from a completed randomized clinical trial.
Potential Reduction in Anxiety
The proposed intervention is expected to produce a rapid reduction in subjective anxiety following brief axillary cold stimulation. Assessment using a validated instrument such as the State–Trait Anxiety Inventory (STAI) could be used to determine changes in acute anxiety before and after the intervention. A reduction in post-intervention anxiety scores would provide preliminary evidence of a possible short-term calming effect. However, the magnitude of any such reduction should be established through prospective clinical investigation rather than assumed from the conceptual model.
Potential Physiological Responses
Brief exposure to cold may influence autonomic physiological responses, including heart rate, respiratory pattern, and subjective perception of bodily arousal. The proposed framework anticipates that some individuals may experience a reduction in physiological arousal following axillary stimulation. Continuous or standardized measurement of heart rate and respiratory rate before and after the intervention would be required to determine whether these changes are statistically and clinically meaningful.
Perceived Emotional Calmness
A further anticipated outcome is an improvement in subjective emotional calmness and reduction in emotional tension. Participants in a future pilot study could rate perceived stress, tension, and relaxation using standardized visual analogue scales or validated psychological instruments. An improvement in these measures immediately following the intervention would support the hypothesis that brief axillary cold exposure may have a short-term self-regulatory effect.
Neurophysiological Interpretation
The proposed findings are consistent with a possible neurophysiological pathway in which localized cold stimulation activates cutaneous cold-sensitive afferent pathways and alters autonomic and sensory processing. The resulting sensory input may influence sympathetic and parasympathetic regulation and may temporarily redirect attention away from anxiety-related cognitive processing toward an immediate physical sensation. However, the precise contribution of vagal activity, sympathetic modulation, thermoreceptor activation, and central autonomic networks remains to be experimentally established.
Overall Findings
Overall, the conceptual framework suggests that brief axillary cold application may have potential as a simple, inexpensive, and readily accessible technique for short-term regulation of acute emotional distress. The principal outcomes proposed for future investigation include reduction in subjective anxiety, decreased emotional tension, changes in physiological arousal, and increased perceived calmness.
These observations should be regarded as hypothesis-generating rather than definitive clinical evidence. Appropriately designed randomized controlled studies with adequate sample sizes, validated psychological instruments, objective physiological measurements, appropriate statistical analysis, and clearly defined safety criteria are required to establish the effectiveness and clinical applicability of axillary ice application for acute anxiety and stress.
DISCUSSION
Overall, the conceptual framework provides a testable hypothesis rather than evidence of therapeutic efficacy. Its contribution is to organize a plausible set of physiological and psychological mechanisms and define measurable outcomes for future research. Direct clinical validation is required before axillary ice application can be recommended as an evidence-based intervention for anxiety or stress.
Future research should therefore begin with small, ethically approved feasibility studies followed by adequately powered randomized controlled trials. Studies should use standardized axillary cooling procedures, appropriate control conditions, validated anxiety measures, heart rate variability, respiratory rate, blood pressure, skin conductance, and, where feasible, endocrine biomarkers such as cortisol. Blinded outcome assessment and prespecified statistical analyses would strengthen the evidence. Comparative studies against breathing exercises, grounding techniques, mindfulness, or other established non-pharmacological strategies could help determine whether the intervention provides any clinically meaningful additional benefit.
The major limitation of the present work is the absence of direct clinical evidence. The manuscript is a narrative review with a conceptual framework rather than a clinical trial or systematic review. The literature search was designed to identify biologically relevant evidence, but no formal systematic-review methodology or quantitative synthesis was undertaken. In addition, the proposed protocol does not establish the optimal temperature, duration, frequency, laterality, timing, or patient population. The conceptual model also cannot determine whether any future effect would be attributable to autonomic modulation, interoceptive attention, expectancy, placebo effects, or another mechanism.
Another important consideration is that acute anxiety can sometimes represent a manifestation of a medical or psychiatric condition requiring assessment and treatment. Axillary cold application should not be presented as a replacement for established psychological or medical care, particularly for persistent, severe, recurrent, or clinically impairing anxiety.
From a practical perspective, the proposed intervention is inexpensive and potentially accessible. Nevertheless, convenience should not be equated with clinical safety or effectiveness. Direct application of ice to skin can produce pain, cold injury, skin damage, or excessive local cooling if used improperly. Future studies should therefore use a controlled cold source, protective material between the cold source and skin, predefined exposure duration and temperature limits, continuous monitoring of participant comfort, and clear stopping criteria. Individuals with conditions that could make localized cold exposure inappropriate should be excluded according to a prospectively defined safety protocol.
Interoceptive processing may provide another possible explanation for a perceived reduction in acute distress. A sudden, salient cold sensation can redirect attention toward immediate bodily sensations and away from repetitive anxious thoughts. This possibility is consistent with broader theories of interoception and emotional regulation, but it has not been demonstrated specifically for axillary ice application.
The anatomical characteristics of the axillary region may make it an interesting site for investigation because of its cutaneous sensory innervation and superficial vascular structures. Nevertheless, anatomical proximity alone does not establish direct vagus nerve stimulation. The present framework consequently uses the more cautious concept of indirect sensory and autonomic modulation rather than claiming direct vagal activation.
Cold stimulation can generate strong sensory and autonomic responses, and previous research on different forms of cold exposure provides a rationale for investigating whether localized cooling might affect physiological arousal. However, evidence from facial cooling, whole-body exposure, cryotherapy, or cold application in procedural settings cannot automatically be generalized to the axillary site. The proposed relationship between axillary cooling and parasympathetic or vagal activity is therefore mechanistically plausible but remains unconfirmed for this specific intervention.
The present manuscript develops a conceptual framework for investigating whether brief axillary cold application could influence acute anxiety, emotional tension, and stress. The framework is informed by literature concerning cold sensory stimulation, autonomic regulation, interoception, and stress physiology. Importantly, no participants were enrolled, and no experimental data were collected. Therefore, the manuscript does not demonstrate that axillary ice application reduces anxiety, lowers heart rate, increases calmness, activates the vagus nerve, or suppresses the HPA axis.
CONCLUSION
This narrative review presents a conceptual framework for investigating brief axillary ice application as a potential complementary strategy for acute anxiety, emotional tension, and stress. Existing literature concerning cold stimulation, autonomic regulation, interoception, and stress physiology provides a rationale for experimental investigation, but it does not establish the effectiveness of axillary ice application specifically.
No participants were enrolled, and no primary data were collected for the present manuscript. Consequently, the previously stated numerical reductions in anxiety, heart rate, and perceived calmness have been removed and should not be interpreted as empirical findings. Similarly, proposed effects involving parasympathetic or vagal activity and hypothalamic–pituitary–adrenal axis modulation should be regarded as hypotheses requiring direct experimental testing.
The proposed intervention may be attractive because of its simplicity, accessibility, and low cost; however, its safety parameters, optimal application protocol, and clinical effectiveness remain uncertain. Future ethically approved studies should determine the appropriate temperature, duration, frequency, and treatment conditions while using validated psychological measures and objective physiological outcomes, including heart rate variability and other autonomic biomarkers.
In conclusion, axillary cold application represents a scientifically testable hypothesis for a simple non-pharmacological approach to acute emotional distress. The present conceptual framework provides a basis for future feasibility studies and randomized controlled trials, but direct clinical evidence is required before the intervention can be recommended as an evidence-based treatment or routinely used for anxiety or stress management.
ETHICAL CONSIDERATIONS
No human participants were enrolled, and no human-subject data were collected for this conceptual manuscript; therefore, there was no participant intervention requiring ethical approval for the work reported here. Any future clinical investigation involving axillary cold application must obtain approval from an appropriate institutional ethics committee or review board, obtain informed consent, define safety-monitoring procedures, and establish clear exclusion and stopping criteria before recruitment.
ACKNOWLEDGMENT
The authors sincerely thank all participants and contributors whose support made this work possible. Special appreciation is extended to Dr. Naweed Imam Syed, Professor, Department of Cell Biology, University of Calgary, for his valuable guidance, constructive suggestions, and continuous encouragement throughout the preparation of this manuscript.
CONFLICT OF INTEREST
The authors declare that they have no conflicts of interest related to this work.
FUNDING
This research received no specific grant from any funding agency in the public, commercial, or not-for-profit sectors.
REFERENCES
- American Psychiatric Association . Diagnostic and Statistical Manual of Mental Disorders. 5th ed. Washington (DC): American Psychiatric Association; 2013.
- Kessler RC, Ruscio AM, Shear K, Wittchen HU. Epidemiology of anxiety disorders. Behavioral neurobiology of anxiety and its treatment. 2009:21-35. [Crossref] [Google Scholar]
- Thayer JF, Lane RD. A model of neurovisceral integration in emotion regulation and dysregulation. Journal of affective disorders. 2000;61(3):201-16. [Crossref] [Google Scholar] [PubMed]
- Porges SW. The polyvagal theory: phylogenetic substrates of a social nervous system. International journal of psychophysiology. 2001;42(2):123-46. [Crossref] [Google Scholar] [PubMed]
- McEwen BS. Physiology and neurobiology of stress and adaptation: central role of the brain. Physiological reviews. 2007;87(3):873-904. [Crossref] [Google Scholar] [PubMed]
- Craig AD. How do you feel—now? The anterior insula and human awareness. Nature reviews neuroscience. 2009;10(1):59-70. [Crossref] [Google Scholar] [PubMed]
- Craig AD. How do you feel? Interoception: the sense of the physiological condition of the body. Nature reviews neuroscience. 2002;3(8):655-66. [Crossref] [Google Scholar] [PubMed]
- Castellani JW, Tipton MJ. Cold stress effects on exposure tolerance and exercise performance. Comprehensive Physiology. 2016 Jan 17;6(1):443-69. [Google Scholar]
- Huttunen P, Rintamäki H, Hirvonen J. Effects of cold exposure on hormonal stress responses. Int J Circumpolar Health. 2004;63(4):373–380. [PubMed]
- Van Diest I, et al. Autonomic dysregulation in anxiety disorders. Biol Psychol. 2009;82(2):113–120.
- Critchley HD, Wiens S, Rotshtein P, Öhman A, Dolan RJ . Neural systems supporting interoceptive awareness. Nature neuroscience. 2004;7(2):189-95. [Crossref] [Google Scholar] [PubMed]
- Paulus MP, Stein MB. Interoception in anxiety and depression. Brain structure and Function. 2010;214(5):451-63. [Crossref] [Google Scholar] [PubMed]
- Brewer JA, et al. Interoceptive awareness and anxiety regulation. Biol Psychiatry. 2016;79(9):747–756.
- Feinstein JS, Buzza C, Hurlemann R, Follmer RL, Dahdaleh NS, et al. Fear and panic in humans with bilateral amygdala damage. Nature neuroscience. 2013;16(3):270-2. [Crossref] [Google Scholar] [PubMed]
- Noble DJ, Hochman S. Vagus nerve stimulation for anxiety disorders. Auton Neurosci. 2019;220:102–110. [PubMed]
- Quintana DS, et al. Heart rate variability and emotion regulation. Psychophysiology. 2016;53(3):367–380.
- Lehrer PM, et al. Biofeedback and autonomic control in anxiety. Appl Psychophysiol Biofeedback. 2007;32(2):155–165. [PubMed]
- Gross JJ. The emerging field of emotion regulation: An integrative review. Review of general psychology. 1998;2(3):271-99. [Crossref] [Google Scholar]
- Brown RP, Gerbarg PL. Sudarshan Kriya yogic breathing in the treatment of stress, anxiety, and depression: part I—neurophysiologic model. The Journal of Alternative and Complementary Medicine: Paradigm, Practice, and Policy Advancing Integrative Health. 2005;11(1):189-201. [Crossref] [Google Scholar] [PubMed]
- Chrousos GP. Stress hormones and emotional regulation. Endocrinol Metab Clin North Am. 2000;29(1):13–25. [PubMed]
- RD, et al. Neural correlates of emotional awareness. J Psychosom Res. 2009;67(2):89–95. [PubMed]
- Boucsein W. Electrodermal activity. Springer science & business media; 2012. [Crossref] [Google Scholar]
- Hofmann SG, et al. Anxiety regulation strategies. Clin Psychol Rev. 2012;32(5):405–415.
- Park J, et al. Somatic interventions in anxiety management. Front Psychol. 2021;12:628.
- Woolfolk RL, Lehrer PM. Principles and practice of stress management. (No Title). 1984. [Google Scholar]